3rd-degree (complete) AV block
Also called complete heart block, third-degree heart block.
Complete AV dissociation. P waves march out at their own regular rate and wide escape complexes march out at a separate, slower rate, with no relationship between them. The PR is different on every beat.
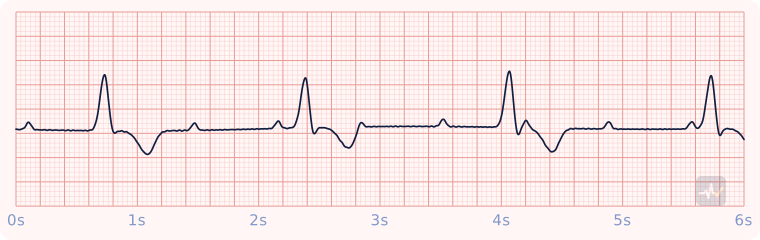
How to identify 3rd-degree (complete) AV block
- Rate
- Atrial faster than ventricular. The escape runs 40-60 if junctional, 20-40 if ventricular
- Rhythm
- P-P regular and R-R regular, independently
- P waves
- Regular, marching through the QRS and T waves
- PR interval
- Different on every beat: no relationship
- QRS
- Wide here (a ventricular escape)
- Clincher
- Two rhythms that ignore each other: AV dissociation.
Rhythms it gets mistaken for
3rd-degree (complete) AV block vs 2nd-degree type II (Mobitz II)
3rd-degree (complete) AV block has no relationship between the P waves and the QRS complexes. With Mobitz II you would see a PR interval that stays the same, then a QRS that drops without warning. It also has a wide QRS, 0.12 s or more, while Mobitz II would show a narrow QRS, under 0.12 s. A wide QRS means the signal started in the ventricles or got there through an abnormal path. It also has a regular rhythm, while Mobitz II would show pauses where a QRS drops. How to spot Mobitz II: A constant PR, then a QRS drops without warning. It sits below the node and can progress to complete block.
3rd-degree (complete) AV block vs Idioventricular rhythm
3rd-degree (complete) AV block has regular P waves, with more P waves than QRS complexes. With an idioventricular rhythm you would see no upright P wave in front of the QRS. It is an AV block: the P waves come from the SA node, and the problem is the P-to-QRS relationship. How to spot an idioventricular rhythm: Wide, slow, no P waves: the ventricle escaping on its own.
3rd-degree (complete) AV block vs 2nd-degree type I (Wenckebach)
3rd-degree (complete) AV block has no relationship between the P waves and the QRS complexes. With Wenckebach you would see a PR interval that gets longer beat after beat until a QRS drops. It also has a wide QRS, 0.12 s or more, while Wenckebach would show a narrow QRS, under 0.12 s. A wide QRS means the signal started in the ventricles or got there through an abnormal path. It also has a regular rhythm, while Wenckebach would show pauses where a QRS drops. How to spot Wenckebach: Longer, longer, longer, drop. Usually nodal and usually benign.
Treatment by certification level
Open your level. Treat the patient, not the strip.
Paramedic
Stable
Stable, but watch it closely.
- Monitor, IV access, transport and reassess.
- Put the pads on now so pacing is ready.
- If it becomes symptomatic, go to pacing or dopamine 5-20 mcg/kg/min, or epinephrine 2-10 mcg/min, titrated to effect. Do not rely on atropine: the block sits below where it acts.
Unstable
Symptomatic high-grade block: go to pacing.
- Do not rely on atropine: the block sits below where it acts. Atropine 1 mg may be tried while the pads go on, but it never delays pacing.
- Transcutaneous pacing (rate 60-80, mA up until capture, then slightly above). Confirm mechanical capture with a femoral pulse, not a carotid.
- Sedation and analgesia; recheck the blood pressure once captured.
- No capture or still poorly perfusing: dopamine 5-20 mcg/kg/min, or epinephrine 2-10 mcg/min, titrated to effect.
- Expert consultation: this patient may need a transvenous pacer.
AEMT
Stable
Pulse present and stable.
- Oxygen only if hypoxic or short of breath, IV access, monitoring.
- Acquire and transmit a 12-lead ECG. Interpreting it is a Paramedic skill.
- Transport and reassess. Request a paramedic if the patient worsens.
Unstable
Symptomatic bradycardia with a pulse.
- Support oxygenation and ventilation, establish IV access, and move the patient.
- Expedited transport, with a paramedic intercept if that is genuinely faster than reaching the hospital.
Synchronized cardioversion and pacing are Paramedic-only, so the AEMT has no electrical option for a patient with a pulse. Never put the AED on this patient.
EMT
Stable
Pulse present: assess and support.
- Treat the patient, not the rhythm name: airway, breathing, circulation, vital signs.
- Oxygen if the SpO2 is under 94%, the patient is short of breath, or shows signs of shock.
- Request ALS and transport promptly. Reassess on the way.
An AED goes only on a patient who is unresponsive, not breathing and pulseless. It cannot feel a pulse, so on a patient with a pulse it can advise a shock that would do harm.
Unstable
Pulse present but poorly perfusing: this patient needs ALS fast.
- Treat the patient, not the rhythm name: airway, breathing, circulation, vital signs.
- Oxygen if the SpO2 is under 94%, the patient is short of breath, or shows signs of shock.
- Request ALS and transport promptly. Reassess on the way.
An AED goes only on a patient who is unresponsive, not breathing and pulseless. It cannot feel a pulse, so on a patient with a pulse it can advise a shock that would do harm.